
Lip Filler Blanching can be alarming, especially when treated lips turn pale, cool, or unusually painful. In 2026, safer filler care still depends on anatomy, product knowledge, careful technique, and rapid clinical judgment. Blanching may indicate pressure on a small vessel, reduced blood flow, or temporary tissue compression. It should never be dismissed as a normal cosmetic effect.
Experienced, qualified injectors assess lip structure, previous treatments, skin color, vascular risk, and the patient’s medical history before injecting. They use conservative volumes, appropriate products, gentle placement, and continuous observation. A mirror, bright lighting, and clear communication can reveal subtle changes early. Patients should report increasing pain, whitening, dusky discoloration, coldness, or delayed capillary refill immediately. Waiting for the appointment to end may create unnecessary risk.
Prevention is not a single trick. It involves choosing a regulated clinic, confirming the practitioner’s credentials, discussing realistic goals, and following aftercare instructions carefully. Evidence and professional guidance continue to evolve, so confident claims deserve scrutiny. Even skilled injectors cannot remove every complication. That is an uncomfortable truth.
This guide explores practical ways to reduce Lip Filler Blanching, recognize warning signs, and support safer decisions. It does not replace an in-person medical assessment. If symptoms appear after treatment, contact the injector urgently or seek appropriate medical care. Acting early matters.
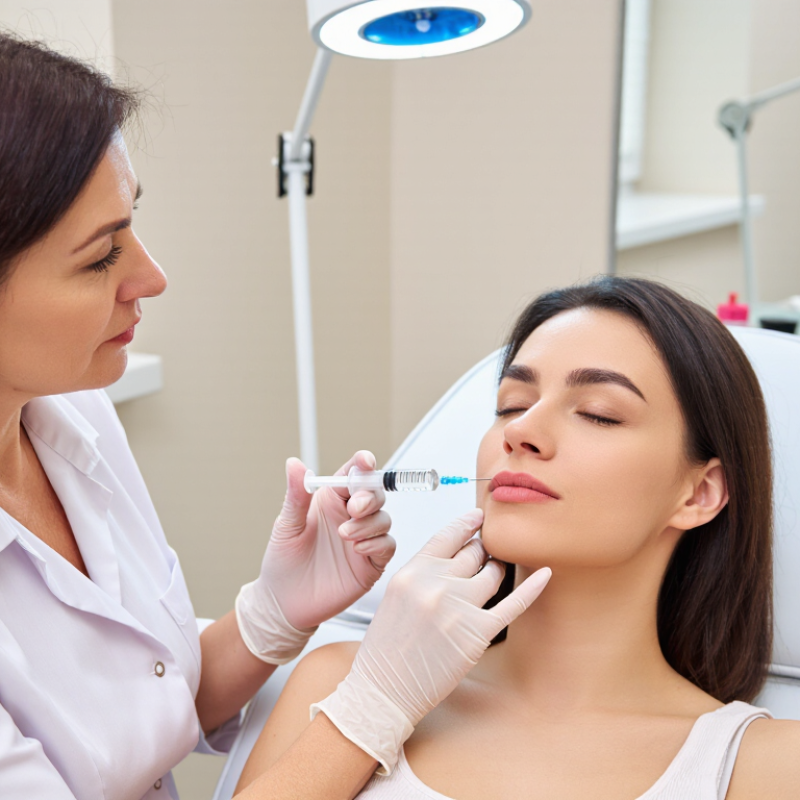
How to Prevent Lip Filler Blanching in 2026?
Blanching means reduced colour in the lip, but it does not always mean vascular ischaemia. Transient pallor can follow needle pressure, local anaesthetic, cooling, or temporary tissue compression. The area often remains warm, with mild discomfort and improving colour within minutes. Good lighting matters. So does patience.
Vascular ischaemia is more concerning. Look for severe or escalating pain, persistent whitening, mottled skin, coolness, delayed capillary refill, or colour changes beyond the injection area. Capillary refill alone is not enough. Compare both sides and assess the pattern repeatedly. A quiet-looking lip can still deteriorate. If symptoms persist or progress, stop injecting and seek urgent assessment from an appropriately trained medical professional.
Prevention starts with detailed anatomy, conservative product placement, slow injection, and minimal pressure. Use small amounts and reassess between deposits. Avoid injecting through visibly compromised tissue. A needle aspiration result cannot guarantee safety, so it should never replace anatomical awareness. Clear emergency protocols should be available before treatment begins.
I have learned that rushing makes subtle signs easier to miss. Even experienced practitioners can misread early pallor, especially under bright lights. Documenting colour, pain, temperature, and refill over time creates a more reliable clinical picture. Patients should also receive clear aftercare instructions and know which changes require immediate contact.
| Assessment dimension | Transient injection-related pallor | Possible vascular ischaemia | What to do immediately |
|---|---|---|---|
| Appearance | Small, localised pale area directly around the needle or cannula track; colour returns promptly as pressure is released. | Persistent or expanding pallor, mottled or reticular colour change, dusky skin, or a distribution that does not match the injection point. | Stop injecting. Compare both sides of the lip and document the colour change with time-stamped photographs. |
| Pain pattern | Brief pressure, pinching, or needle discomfort that settles quickly and is proportional to the procedure. | Severe, escalating, unusual, or disproportionate pain; pain may precede visible skin changes, although reduced sensation can also occur. | Ask the patient to rate pain and describe its location. Treat unexpected or increasing pain as a warning sign requiring urgent assessment. |
| Capillary refill and temperature | Normal warmth and colour return after pressure is removed; capillary refill remains comparable with the untreated side. | Delayed or absent refill, cool skin, or a clear difference from the opposite side. Capillary refill should support, not replace, the overall clinical assessment. | Recheck colour, warmth, sensation, and refill repeatedly. Do not rely on a single normal reading if symptoms are evolving. |
| Timing | Appears during needle pressure or product placement and improves rapidly after the instrument is withdrawn or pressure is reduced. | Persists, worsens, or spreads over minutes to hours; delayed deterioration is possible even when the initial appearance is subtle. | Remain with the patient during observation and arrange urgent clinical review if the abnormal colour or pain does not promptly resolve. |
| Risk-reduction before treatment | Use a detailed facial vascular and medical history, confirm informed consent, use appropriate aseptic technique, select conservative volumes, inject slowly with minimal pressure, and avoid injecting through areas of active inflammation or infection. | Only appropriately trained, licensed clinicians should perform treatment, with an emergency plan, relevant medication access, and a clear pathway for urgent specialist referral. | |
| Technique considerations | Use slow, low-pressure deposition, frequent needle repositioning, small aliquots, and continuous observation of skin colour and patient comfort. Avoid excessive tissue distension and avoid bolus placement in high-risk vascular planes. | Never continue injecting to “test” an area that has become pale, painful, mottled, or otherwise suspicious. | |
| Suspected hyaluronic-acid filler vascular compromise | No specific vascular treatment is usually required when pallor resolves promptly and the examination remains normal. | Treat as an emergency. Persistent blanching, livedoid change, abnormal refill, escalating pain, or tissue cooling requires immediate clinician-led evaluation. | Follow the injector’s emergency protocol and seek urgent expert help. For hyaluronic-acid filler, trained clinicians may use hyaluronidase according to current professional guidance; treatment must not be delayed while waiting for skin breakdown. |
| Eye or neurological symptoms | Not expected from uncomplicated local injection-related pallor. | Visual disturbance, eye pain, ophthalmoplegia, severe headache, facial weakness, confusion, or other neurological symptoms may indicate a serious vascular event. | Call emergency services immediately and activate the local emergency referral pathway. Do not allow the patient to drive themselves. |
| Follow-up | Provide routine aftercare instructions and advise the patient to report persistent colour change, increasing pain, unusual swelling, blistering, or skin breakdown. | Arrange documented reassessment until symptoms and tissue perfusion are stable; monitor for delayed ulceration or necrosis. | Give written contact instructions and ensure the patient knows which symptoms require immediate emergency care. |
Clinical note: Blanching alone is not diagnostic. The combination of persistence, pain, mottling, delayed refill, coolness, sensory change, progression, and ocular or neurological symptoms should be treated as possible vascular compromise until assessed by an appropriately trained clinician.
Blanching means reduced colour. It may be temporary. Needle pressure, cooling, anaesthetic, or tissue compression can cause it. The lip may stay warm. Colour often returns within minutes. Still, monitor it carefully.
Temporary pallor usually improves quickly. The area may remain warm, with mild discomfort. Ischaemia may cause severe pain, persistent whitening, mottling, coolness, or delayed refill. Compare both sides. Recheck repeatedly.
Stop injecting immediately. Do not wait for bruising. Seek urgent assessment from an appropriately trained medical professional. A quiet-looking lip can worsen.
Lip arteries can be only 1–2 millimetres wide. Their positions vary between people. Some lie near the lip border. Others run deeper in the muscle. Anatomy is a guide, not a guarantee.
Real-time ultrasound may help identify larger vessels. It can be useful when scars, previous treatment, or asymmetry change the anatomy. It cannot remove all risk. I would not treat it as perfect.
No. A negative aspiration result cannot guarantee safety. Careful anatomy, slow placement, small deposits, and reassessment remain important. This is easy to underestimate.
Seek urgent help for increasing pain, persistent pallor, cool skin, mottling, or delayed capillary refill. Colour changes outside the injection area also matter. Vision changes need immediate eye assessment.
Patients should know which changes require immediate contact. Give a clear emergency contact route. Explain pain, colour, warmth, and swelling changes. Written instructions help. People forget details under stress.
Use conservative placement and minimal pressure. Inject slowly. Use small amounts. Reassess between deposits. Avoid visibly compromised tissue. Keep emergency supplies and clear procedures ready before treatment.
Written observations create a timeline. Record colour, temperature, pain, and refill. Compare both sides. Early signs can be subtle. I may misread them, especially under bright lights. Rechecking is wiser than early reassurance.
Lip Filler Blanching can range from brief, harmless pallor caused by temporary vessel compression to a warning sign of vascular ischaemia. Understanding the difference is essential: transient blanching usually resolves quickly, while persistent whitening, increasing pain, coolness, mottling, or delayed capillary refill may indicate compromised blood flow. Although vascular occlusion is uncommon, reported rates for hyaluronic acid fillers range from approximately 0.01% to 1%, so careful prevention and monitoring are important.
Safe practice begins with detailed anatomical planning, particularly around labial arteries that may measure only 1–2 mm and can vary in position. Injecting small aliquots slowly, using minimal pressure, and reassessing tissue response between deposits can reduce risk. If ischaemia is suspected, stop injecting, evaluate circulation promptly, and follow an established pulsed hyaluronidase response protocol for hyaluronic acid filler complications. Early recognition, clear documentation, and timely clinical management offer the best chance of restoring blood flow and limiting tissue injury.
